
Why a Thoracic Disc Prolapse Needs a Completely Different Surgery
How common is thoracic disc herniation compared to lumbar or cervical?
Thoracic disc herniation is considerably less common, representing a small fraction of all symptomatic disc herniations treated. This relative rarity is related to the greater structural stability of the thoracic spine, provided by the rib cage.
What are the symptoms of a thoracic disc prolapse?
Symptoms depend on the size and location of the herniation but can include mid-back pain, band-like pain around the chest or abdomen (following the distribution of the affected thoracic nerve root), leg weakness, and in severe cases, symptoms of spinal cord compression including gait disturbance and bladder or bowel dysfunction.
Is single lung ventilation safe?
Yes, single lung ventilation is a well-established and safe technique used routinely in thoracic surgery, managed by anaesthetists with specific training in this approach. The remaining ventilated lung is capable of providing adequate gas exchange for the duration of most procedures.
How long is the recovery after thoracotomy for a thoracic disc herniation?
Recovery from a thoracotomy approach involves both the spinal surgery recovery and the chest wall surgery recovery. Most patients require a hospital stay of several days, with a chest drain typically removed within the first few days. Full recovery, including return to normal activity, generally takes several weeks to a few months.
Is there pain after a thoracotomy incision separate from the spine surgery itself?
Yes, the thoracotomy incision itself, involving spreading of the ribs, can cause significant post-operative pain distinct from any pain related to the underlying spinal condition. This is managed with a combination of pain medication and, in some cases, specific nerve block techniques targeting the intercostal nerves.
Can all thoracic disc herniations be treated without surgery?
Many thoracic disc herniations, particularly those without significant spinal cord compression or progressive neurological deficit, can be managed conservatively with the same principles applied to lumbar disc herniation: physiotherapy, pain management, and monitoring. Surgery is reserved for those with significant or progressive neurological compromise, or severe symptoms unresponsive to conservative management.
Will I need a chest tube after thoracic disc surgery?
Yes, if the surgeon enters the chest cavity through a transthoracic or VATS approach, a chest tube will be placed before closing the incision. The tube drains any fluid or air from the chest cavity and allows the lung to fully re-expand. The tube typically stays in place for 1 to 4 days, depending on the amount of drainage. Once drainage decreases to acceptable levels, the tube is removed. Removal is quick but can be briefly uncomfortable.
What are the chances of permanent lung damage from thoracic spine surgery?
Permanent lung damage is rare with modern techniques and careful surgical and anesthesia management. Most patients recover full or near-full pulmonary function within a few weeks to months after surgery. Some studies report a modest (around 10%) temporary reduction in pulmonary function after thoracotomy, but this typically improves with time. Risk factors for pulmonary complications include smoking, pre-existing lung disease, prolonged surgery, and obesity. Patients can minimize risk by stopping smoking before surgery and actively participating in breathing exercises after surgery.
Of the three regions of the spine, the thoracic spine presents the most anatomically constrained surgical environment. Above it, the cervical spine has the spinal cord to navigate around but relatively accessible surrounding soft tissue. Below it, the lumbar spine has individual nerve roots rather than the cord itself, allowing more surgical flexibility. The thoracic spine sits between two of the body’s most critical structures, the spinal cord behind and the heart and great vessels in front, leaving surgeons with a genuinely narrow anatomical corridor and a surgical approach unlike anything used elsewhere in the spine.
Dr. Sherief Elsayed, Consultant Spine Surgeon in Dubai, describes exactly what this approach involves and why it is dictated entirely by the anatomy that surrounds the thoracic disc space.
Why the Standard Approaches Do Not Work Here
Dr. Sherief Elsayed explains the fundamental problem directly: “If you have a disc prolapse in your thoracic spine, I need to approach it completely differently.”
Why not from the back?
“The reason we need to come from the sides is I can’t come from the back because the spinal cord is in the way.”
As established in the earlier article comparing lumbar and cervical disc surgery, the presence of the spinal cord directly behind the disc space rules out the straightforward posterior approach used in the lower lumbar spine, where individual nerve roots of the cauda equina can be gently retracted. In the thoracic spine, as in the cervical spine, the full spinal cord occupies the canal, and any attempt to retract it to access a disc prolapse from directly behind risks catastrophic and irreversible neurological injury.
Why not from the front?
“I can’t come directly from the front because the heart is in the way.”
This is the anatomical constraint that is unique to the thoracic spine and does not apply to the cervical or lumbar regions. The thoracic vertebral bodies sit directly behind the heart, the great vessels, and the mediastinal structures. A direct anterior approach through the chest, attempting to reach the thoracic spine the same way an anterior cervical approach reaches the neck, would require working directly through or immediately adjacent to the beating heart, which is neither anatomically feasible nor safe using standard surgical technique.
With both the posterior and direct anterior approaches ruled out by critical anatomical structures, the only remaining pathway is from the side.
The Surgical Approach: A Lateral Thoracotomy
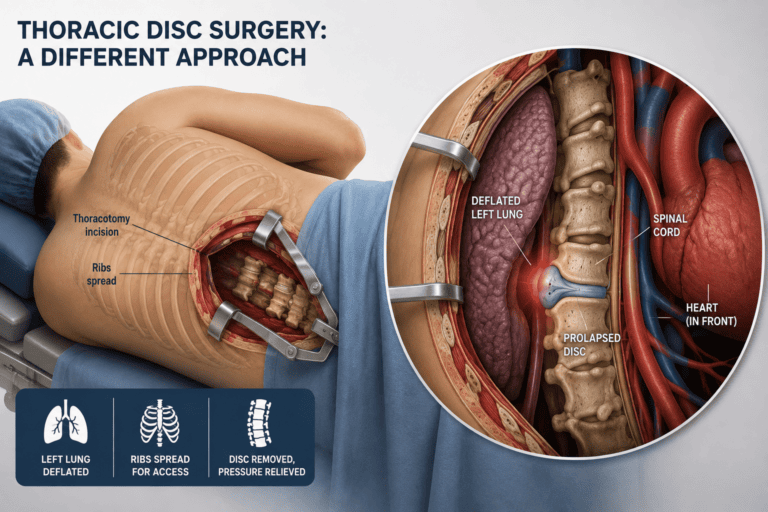
Dr. Sherief Elsayed describes the specific technique used: “What I do is I have the patient on their side, typically left side up. What I do is I make an incision called a thoracotomy in order to go down onto the rib cage. Spread the ribs apart, occasionally taking a rib out, and then we deflate one lung, the left lung, leaving the right lung doing all the work, and then going down onto the spine, taking out the prolapsed disc before re-inflating the lung and closing up.”
This description outlines the essential steps of a transthoracic approach to the thoracic spine, one of the more technically demanding procedures in all of spinal surgery because it requires coordinated expertise across spinal surgery, thoracic surgery, and specialised anaesthesia.
Patient positioning:
The patient is positioned in the lateral decubitus position, lying on their side. This positioning allows gravity to assist in retracting the lung away from the operative field once it has been deflated, and provides the surgeon with the most direct lateral access to the thoracic vertebral bodies.
The thoracotomy incision:
A thoracotomy is an incision made between the ribs to gain access to the chest cavity. The specific rib level chosen depends on which thoracic vertebral level requires access, as the surgeon must approach at a level that provides a direct trajectory to the target disc space.
Rib spreading and occasional rib removal:
Once the chest cavity is entered, the ribs are spread apart using a specialised retractor to create adequate working space. In some cases, removing a short segment of a rib provides additional access and can also serve as a source of autologous bone graft material for the subsequent disc space reconstruction, if fusion is planned.
Single lung ventilation:
This is one of the most distinctive elements of thoracic spine surgery and requires close collaboration with the anaesthetic team. A specialised double-lumen endotracheal tube allows the anaesthetist to selectively ventilate only one lung while the other is deliberately deflated. As Dr. Sherief Elsayed describes, the left lung is deflated in this approach, allowing it to collapse away from the surgical field and be gently retracted, while the right lung continues to provide all of the patient’s gas exchange throughout the procedure.
This technique, single lung ventilation, is a well-established anaesthetic practice used across thoracic surgery generally, not unique to spinal procedures, but it adds a layer of physiological complexity that is not present in standard posterior lumbar or cervical spinal surgery.
Reaching and treating the disc:
Once the lung has been deflated and retracted and the pleural cavity has been safely navigated, the surgeon works along the lateral aspect of the vertebral bodies to identify the affected disc level and remove the prolapsed material, decompressing the spinal cord from this lateral trajectory rather than from directly behind or in front.
Closure:
Following disc removal and any necessary reconstruction, the lung is re-inflated under direct vision to confirm full expansion, a chest drain is typically placed to manage any air or fluid in the pleural space during the initial recovery period, and the chest wall is closed in layers.
“I Can Feel the Heart Beating”
Dr. Sherief Elsayed adds a striking and honest observation about the proximity to the heart during this procedure: “While I can feel the heart beating when I come in this direction, I’m not actually pushing it out of the way.”
This distinction is anatomically important. The lateral approach to the thoracic spine passes close enough to the mediastinum, the central compartment of the chest containing the heart and great vessels, that the surgeon is genuinely aware of the heart’s proximity and its rhythmic movement throughout the procedure. However, unlike a direct anterior approach, which would require actively displacing or retracting the heart itself, the lateral trajectory does not require any direct manipulation of the heart. The surgeon works alongside this critical structure rather than through or around it, respecting its position rather than needing to move it.
This careful language reflects the genuine precision required in this surgery: close enough to be constantly aware of the heart’s presence, but structured in a way that avoids ever needing to directly interact with it.
Why Thoracic Disc Prolapse Requires This Level of Surgical Complexity
Thoracic disc herniation is considerably less common than lumbar or cervical disc herniation, representing a small minority of all symptomatic disc prolapses. This relative rarity means that fewer surgeons develop extensive experience with this specific anatomical approach compared to the much more commonly performed lumbar and cervical procedures. A Spinal Cord Surgeon in Dubai applies the same risk-benefit reasoning when planning thoracic cord decompression as for cervical procedures.
Why thoracic disc herniations are less common:
The thoracic spine is inherently more stable than the cervical or lumbar spine due to the additional support provided by the rib cage and the reduced range of motion at each thoracic level. This structural stability reduces the mechanical stress placed on thoracic discs compared to the more mobile cervical and lumbar segments, correspondingly reducing the incidence of herniation at these levels.
Why they are still clinically significant when they occur:
When thoracic disc herniation does occur and produces spinal cord compression, the consequences can be severe, given the confined space within the thoracic spinal canal and the limited tolerance of the thoracic cord for additional compression, a vulnerability related to the more tenuous blood supply of the thoracic cord discussed in the earlier article on spinal cord protection during surgery.
A Thoracic Spine Surgeon in Dubai with specific training and experience in this transthoracic approach is essential for patients requiring surgical management of a symptomatic thoracic disc herniation, given both the technical complexity involved and the relative rarity of the condition compared to lumbar and cervical disc disease.
What Are the Risks and Complications of Lung Deflation During Thoracic Spine Surgery?
While lung deflation itself is generally safe when performed by experienced teams, the process of entering the chest cavity and performing one-lung ventilation does carry some risks.
Pulmonary Complications
The most common complications relate to the respiratory system:
Atelectasis: Collapse of small air sacs in the lungs, particularly common in the deflated lung. This usually resolves with deep breathing, coughing, and incentive spirometry after surgery.
Pneumonia: Infection in the lungs can occur post-operatively, especially in patients with compromised lung function or those who have difficulty coughing effectively after surgery.
Pleural Effusion: Fluid accumulation in the chest cavity around the lung. Small effusions often resolve on their own, larger ones may require drainage.
Pneumothorax or Hemothorax: Air (pneumothorax) or blood (hemothorax) can accumulate in the chest cavity if the lung is injured or if there is bleeding. This is why a chest tube is placed at the end of surgery to drain any fluid or air.
Re-Expansion Pulmonary Edema: Rarely, when a lung that has been deflated for a prolonged period is rapidly re-expanded, fluid can leak into the lung tissue causing edema (swelling). This is prevented by re-expanding the lung gradually and periodically inflating it during the procedure.
Prolonged Air Leak: If the lung surface is injured during surgery, air can leak from the lung into the chest cavity. This usually heals on its own but may require keeping the chest tube in place longer.
Other Approach-Related Complications
Intercostal Neuralgia: Damage to the nerves that run along the ribs can cause chronic chest wall pain after surgery. This occurs in a significant percentage of patients after thoracotomy.
Lung Injury: Direct injury to the lung from surgical instruments, though uncommon with careful technique.
Blood Vessel Injury: The thoracic cavity contains major blood vessels. Injury to segmental vessels or even the aorta is possible but rare.
Chylothorax: Injury to the thoracic duct can cause lymphatic fluid to leak into the chest cavity.
Shoulder Dysfunction: Prolonged retraction during surgery can cause temporary or permanent shoulder girdle weakness or pain.
Dr. Sherief Elsayed notes: “These risks are real, which is why we carefully select which patients need an anterior approach. For many thoracic disc herniations, particularly smaller, lateral ones, we can use posterior or lateral approaches that do not require entering the chest cavity. But for large, central, calcified discs, the anterior approach with lung deflation may be the safest way to completely decompress the spinal cord without manipulating it.”
Alternative Approaches for Selected Cases
While the transthoracic approach described here remains the standard for many thoracic disc herniations, particularly larger, centrally located, or calcified discs, minimally invasive alternatives have been developed for appropriately selected cases.
Thoracoscopic (video-assisted) approaches use smaller incisions with a camera and specialised instruments to achieve similar access with reduced chest wall trauma compared to an open thoracotomy, though this technique requires additional specialised training and is not appropriate for all disc pathology.
Posterolateral approaches, including costotransversectomy and the lateral extracavitary approach, access the disc space from a more posterior trajectory while still avoiding direct manipulation of the spinal cord, and may be preferred for more laterally located disc herniations that do not require the fullest anterior exposure that a transthoracic approach provides.
The choice between these approaches depends on the specific characteristics of the disc herniation. A Thoracic Spine Doctor in Dubai will select the most appropriate technique based on the disc location, size, and calcification.
What Should Patients Expect Before, During, and After Thoracic Disc Surgery With Lung Deflation?
Understanding what to expect can reduce anxiety and help patients prepare for thoracic disc surgery.
Before Surgery
Pulmonary Function Testing: Patients may undergo breathing tests to ensure their lungs can tolerate one-lung ventilation.
Cardiac Evaluation: The heart is stressed during one-lung ventilation, so cardiac evaluation may be needed, especially in older patients or those with heart disease.
Smoking Cessation: Patients who smoke should stop at least two weeks before surgery, ideally longer. Smoking dramatically increases the risk of pulmonary complications.
Chest Physiotherapy: Learning breathing exercises and using an incentive spirometer before surgery helps prepare the lungs and facilitates recovery.
Positioning Planning: The surgical team plans the side of approach, the level of incision, and the positioning strategy based on the imaging studies.
During Surgery
The procedure typically takes 3 to 5 hours depending on complexity. Patients are under general anesthesia and have no awareness during surgery. The anesthesia team manages the double-lumen tube and one-lung ventilation. The surgical team carefully dissects through the chest wall, deflates the lung, accesses the spine, removes the disc herniation, places any necessary bone graft or instrumentation, re-expands the lung, places a chest tube, and closes the incision in layers.
After Surgery
Intensive Care Monitoring: Many patients spend the first night in an intensive care unit for close respiratory monitoring.
Chest Tube Management: The chest tube remains in place until drainage decreases, usually 1 to 4 days. While in place, the tube allows the lung to fully re-expand and drains any fluid or air.
Aggressive Pulmonary Hygiene: Deep breathing exercises, coughing (splinting the incision with a pillow), incentive spirometry, and early mobilization are crucial to prevent atelectasis and pneumonia.
Pain Management: Intercostal neuralgia and incisional pain can be significant. Multimodal pain control including epidural analgesia, nerve blocks, and medications helps patients breathe deeply and participate in rehabilitation.
Chest X-Rays: Serial chest X-rays monitor lung re-expansion and detect any complications.
Neurological Monitoring: The primary goal of surgery is spinal cord decompression, so careful neurological examination ensures the surgery achieved its goal without causing injury.
Hospital Stay: Most patients stay in the hospital 4 to 7 days after transthoracic surgery, less for minimally invasive approaches.
Recovery Timeline: Return to light activities typically takes 4 to 6 weeks. Full recovery including return to all normal activities may take 3 to 6 months. Pulmonary function typically returns to near baseline within a few weeks, though some patients report reduced capacity for several months.
Expert Summary
A thoracic disc prolapse cannot be approached the way a lumbar or cervical disc prolapse is treated, because the spinal cord rules out a posterior approach and the heart rules out a direct anterior one. The lateral transthoracic approach, involving single lung ventilation and careful navigation alongside, but never through, the mediastinum, represents one of the most anatomically demanding procedures in spinal surgery. Understanding why this complexity is necessary, rather than optional, helps patients appreciate both the seriousness of thoracic disc surgery when it is needed and the importance of seeking a surgeon with specific experience in this less commonly performed but highly consequential procedure.
Table of Contents
Recent Articles
Why Eight People Were Needed for One Spine Surgery in Dubai
Why Eight People Were Needed for One Spine Surgery in Dubai Does every spinal surgery require exactly eight team members? No, as Dr. Sherief Elsayed explains directly, the specific team
Three Spine Surgery Myths a Dubai Surgeon Wants You to Forget
Three Spine Surgery Myths a Dubai Surgeon Wants You to Forget Is it really safe to walk on the same day as spine surgery? Yes, for the majority of modern
Why Osteoporosis Is Called the Silent Disease in the UAE
Why Osteoporosis Is Called the Silent Disease in the UAE If osteoporosis doesn’t cause pain, how would I know if I needed a DEXA scan? Given the entirely silent nature